
Breast Augmentation – Breast Enlargement
Breast augmentation, also known as augmentation mammoplasty or breast enlargement, is a commonly performed cosmetic surgery worldwide.
In Leeds, the procedure is carried out by Consultant Oncoplastic Breast Surgeon Mr Philip Turton, with over 20 years’ experience in advanced implant planning and natural, personalised results.
The procedure enhances breast size and shape, improves proportion, and restores volume lost through ageing, weight change, or pregnancy.


Why Breast Augmentation Surgery?
Breast augmentation is popular in Leeds and across the UK due to its ability to deliver both physical and emotional transformation. It is one of the most frequently performed cosmetic procedures globally.
Over 10 million women worldwide have undergone the procedure, reflecting its long-established role in aesthetic surgery since the first operation in 1962.
High satisfaction rates are reported, with up to 94% of patients recommending the procedure and implant-specific studies reporting satisfaction rates as high as 97–99%
Reasons for Considering Breast Augmentation Surgery
Breast augmentation is chosen for a wide range of personal and physical reasons. These typically relate to body confidence, proportion, and restoring lost volume.
Aesthetic Concerns
- Naturally small or underdeveloped breasts
- Desire for fuller, more proportionate breast shape
- Breasts that feel out of balance with hips or shoulders
- Preference for improved cleavage or upper fullness
Physical Concerns
- Loss of volume after pregnancy or breastfeeding
- Changes due to ageing or weight loss
- Asymmetry or uneven breast shape
- Breast tissue depletion after earlier uplift surgery
Emotional & Social Impacts
- Low confidence due to breast appearance
- Feeling less feminine or self-assured
- Desire to improve body image and clothing fit
- Restoring confidence after life changes such as childbirth or trauma
The Procedure
Breast augmentation surgery is a detailed procedure that combines expertise in reshaping, resizing, and lifting the breasts.
Here’s what the process entails:
01
Pre-operative consultation and detailed breast assessment.
02
Measurement of chest wall, tissue quality, and breast position. Implant selection based on anatomy and goals.
03
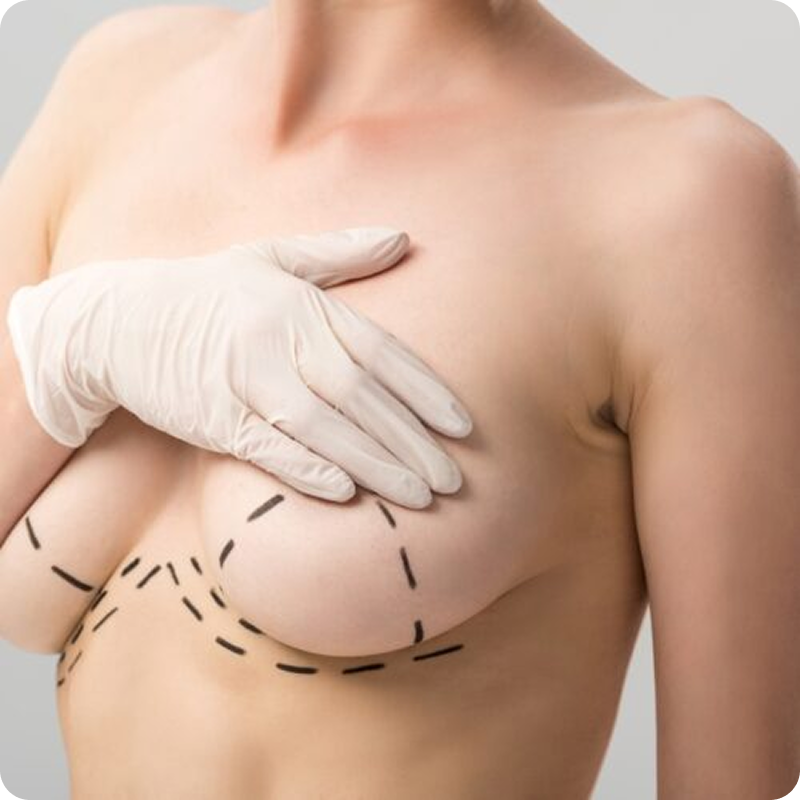
Pre-operative marking in hospital on day of surgery & general anaesthetic administered.
04
Incision made (typically in the inframammary fold). Implant placement & closure of incision with focus on minimal scarring.
DURATION:
Approximately 60 minutes for surgery.
Overnight hospital stay advised.
Safety and Recovery for Breast Augmentation
Breast augmentation is considered a safe procedure when performed by an experienced specialist surgeon in an appropriate hospital setting. However, it is not risk-free.
Risks discussed include:
- Implant rupture
- Capsular contracture
- Infection
- Changes in breast shape over time
- Rare risk of BIA-ALCL
- Sensory changes such as temporary nipple numbness
Post-operative care recommends patients consider structured follow-up monitoring, including MRI surveillance where appropriate.
99%
satisfaction rate for
reconstruction patients
<5%
Symptomatic rupture at 10 years (cohesive implants)
Breast Augmentation Results
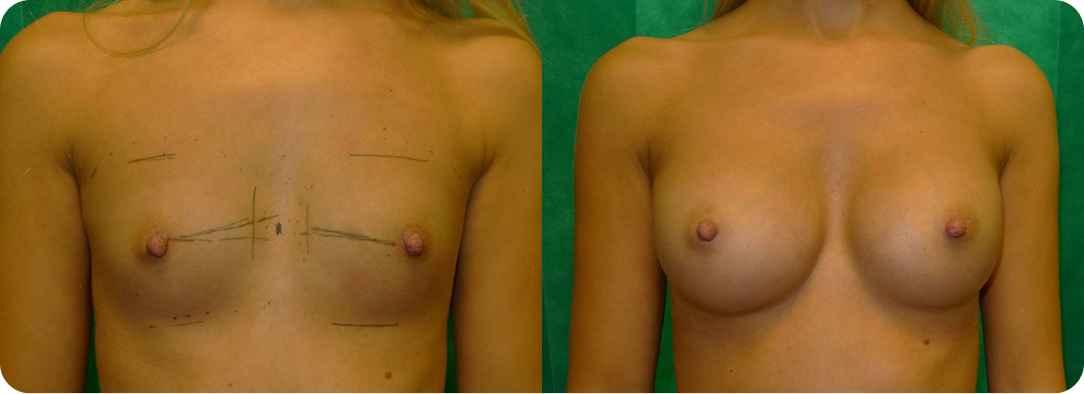
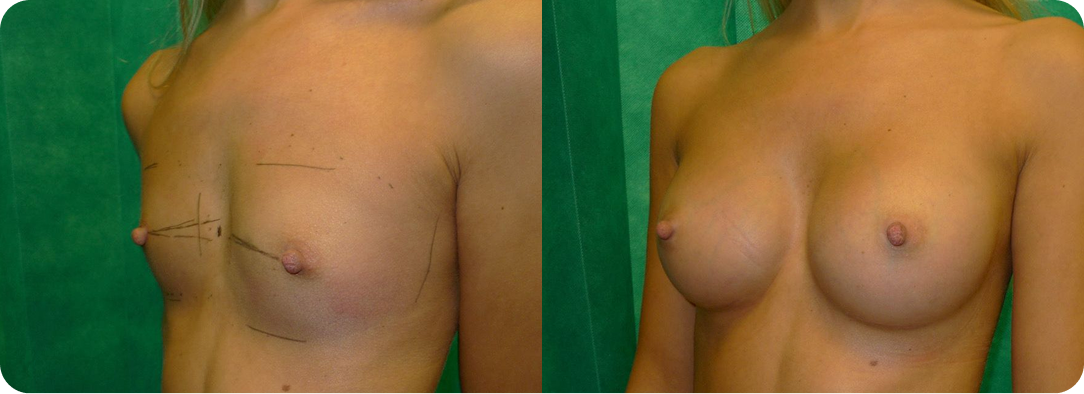
Results are intended to improve breast size, shape, symmetry, and overall body proportion.
Patients typically report:
- Improved self-confidence
- Better body image
- Enhanced clothing fit
- More balanced figure
Results are long-lasting but influenced by ageing, pregnancy, weight change, and implant longevity considerations.
Patient Suitability
Suitable candidates typically include women who:
- Are physically healthy
- Have realistic expectations
- Wish to increase breast size or restore volume
- Experience asymmetry or loss of fullness
- Understand the need for future implant monitoring or replacement
Patients with significant breast sag may require a combined or staged breast uplift procedure for optimal results.


Breast Augmentation Surgery Costs
Standard breast augmentation:
£8,000–£8,500
Rising to £12,500–£14,500 with uplift
Including:
- Comprehensive Surgical care by an expert specialist with over 20 years experience at consultant level.
- The resected breast tissue for histopathology testing by a consultant pathologist where required.
- An overnight hospital stay in a private room on a properly staffed hospital ward
- Comprehensive aftercare and follow-up appointments.
Recovery Timeline
Hospital Stay
Typically 1 night
Return to work
Most patients return to work after ~1 week (2 weeks if physically demanding job)
Pain Management
Most patients find relief with Paracetamol and Ibuprofen within a few days.
Tenderness
Initial tightness and discomfort managed with simple pain relief
Final Results
Scars soften and fade over several months, with optimal results visible in about 6-12 months.
Breast Augmentation Surgery FAQ
The terminology of breast enlargement is important to understand. It is colloquially referred to as a boob job, but we prefer the term breast enlargement and this is the term my patients use with me. When we write about breast enlargement on medical letters or in journals we use the term breast augmentation or augmentation mammoplasty.
We essentially enlarge the breasts to try to improve femininity. The breast has been the symbol of femininity since the earliest time. Often, to a woman, in her perception of her body and her concept of self, the size and shape of her breasts plays a dominant role. Whilst padded bras do give the illusion of increased breast size and they help superficially they can paradoxically cause increased problems for a woman once they are removed and the breasts assume their natural appearance. Breast augmentation has been performed for centuries but the techniques 100-years ago were pretty hopeless involving the transplant of a fatty growth, or the use of experimental materials that were not successful. All of this changed in the early 1960’s and for the last 55-years breast augmentation has become an established surgical technique that is proven to improve a woman’s body image and her perception of self with usually positive psychological effects.
There are generally 2 main groups of women who request this operation. The commonest group of women are represented by mothers of children who were happy with firmer larger breasts before or during pregnancy, or who have found that subsequent to pregnancy and childbirth the breasts have decreased in size and seemingly deflated. This is often with emptiness in the upper half, causing a more scalloped appearance and sometimes combined with loose skin. The lower pole of the breast may overhang the crease under the breast. The second group is represented by young or middle-aged women who are yet to start a family or have decided not to have children, who wish to have breast enlargement as they consider their breasts to be of insufficient size, often disproportionately small to their frame.
Through measurements, 3D imaging, tissue analysis, and surgeon recommendation.
No. Bra sizes are not reliable predictors. Implant choice is based on anatomical assessment.
The implants have an outer silicone shell but virtually all cosmetic breast implants have silicone gel inside. They can be saline-filled but these do not feel as natural. It must be stressed that previous concerns about silicone have proved unfounded in the Independent Review Groups Reports, with no evidence of autoimmune problems, but your surgeon will discuss things with you in more depth and ask any questions that you have. Despite this, Breast implant illness (BII) is a collective term for symptoms that some patients have reported to the MHRA that they believe were caused by their implants and include such things as fatigue, hair thinning, hot flushes, aching joints or muscles, brain fog, skin rashes etc. The FDA and MHRA consider that research and further long term investigation is required to determine if there is a link, so it must be considered possible in some patients. If you have implants and get symptoms like this that you think are caused by your implants you may have to have your implants removed. Natural oil based implants are no longer recommended. The UK market is dominated by silicone filled implants as these give a more natural look and feel. Mr Turton will use one of the high cohesive silicone gel implants, which are far superior to runny silicone.
See our breast implant catalogues.
The choice depends on your breast anatomy, tissue thickness, skin quality, existing breast shape and desired outcome.
An important consideration is whether the implant should be placed in front of or partly beneath the pectoralis muscle. The appropriate implant size and method of creating the implant pocket are also important.
In my practice, these decisions are based on careful clinical assessment, with particular emphasis on appropriate implant dimensions and precise surgical technique.
The patient’s anatomy should determine the operation, rather than the operation being dictated by a particular implant brand or marketed technique.
Around 60 minutes under general anaesthetic. Overnight stay is standard.
All breast augmentation procedures involve some disruption of the natural tissue connections when creating space for an implant.
However, necessary surgical dissection should not be confused with avoidable tissue damage. Careful surgical planning, appropriate implant selection and meticulous pocket creation are intended to minimise unnecessary injury.
In my practice, I favour controlled dissection under direct vision, allowing me to assess the tissues, identify and control bleeding vessels as they are encountered and develop the implant pocket under continuous visual control.
No breast augmentation technique can legitimately claim to avoid tissue disruption altogether.
Tissue preservation is an established principle of good breast surgery, not a new technique or an innovation belonging to a particular implant manufacturer.
In breast augmentation, it involves respecting the patient’s natural anatomy, avoiding unnecessary tissue disruption, selecting implants of appropriate dimensions and creating the implant pocket with careful attention to anatomical structures.
All breast augmentation requires some separation of tissues to accommodate an implant. The term “tissue-preserving” should therefore not be interpreted as meaning that a procedure causes no tissue disruption, or that a particular branded technique has been demonstrated to preserve tissues better than established surgical approaches.
Motiva Preservé is a branded method of breast augmentation in which a blunt separator and an inflatable balloon are used to create the space for an implant in front of the pectoralis muscle.
Much of the implant pocket is formed through blunt mechanical separation and balloon expansion without the surgeon directly visualising the tissues being separated.
Although promoted as a tissue-preserving technique, this method has not been convincingly demonstrated through robust independent comparative studies to cause less tissue injury or produce better long-term outcomes than carefully performed conventional breast augmentation under direct vision.
Prepectoral breast augmentation itself is not new and has been performed using established surgical techniques for decades.
Philip Turton does not offer Motiva Preservé, favouring controlled surgical dissection under direct vision.
Includes infection, rupture, capsular contracture, asymmetry, and rare lymphoma risk (BIA-ALCL).
Implants are not lifetime devices. Many patients consider replacement around 10 years.
Usually mild discomfort/tightness. Managed with paracetamol and ibuprofen.
Breast augmentation can be performed under local anaesthesia, sometimes combined with sedation, in appropriately selected patients. However, avoiding general anaesthesia does not automatically make an operation safer or less invasive.
Local anaesthetic drugs have recommended maximum doses, and excessive dosing or inadvertent injection into a blood vessel can cause potentially serious systemic toxicity. Sedation also carries risks, including respiratory depression and airway obstruction, and requires appropriate monitoring, trained personnel and the ability to manage airway emergencies. These considerations are particularly important when sedation is administered without an anaesthetist present.
In my practice, I favour general anaesthesia for breast augmentation, with a dedicated consultant anaesthetist responsible for the patient’s anaesthetic care. This provides patient comfort, appropriate airway management and the operating conditions I consider most suitable for meticulous surgical dissection and precise implant placement.
Local anaesthesia and sedation can be safe when administered appropriately, but they should not be presented as inherently safer than general anaesthesia simply because the patient remains conscious or avoids a general anaesthetic.
The choice of anaesthesia should be based on an individual assessment of safety, patient comfort and the requirements of the operation, rather than the marketing of a particular technique.
Usually after 1 week (longer if physically demanding).
Yes, in selected cases depending on degree of sagging, either staged or combined.
Ptosis (sagging) is the medical term for nipples that have dropped below their original position. There are various grades and in the worst cases, they can actually be pointing directly at the floor.
Breast augmentation cannot correct anything other than the mildest case of ptosis. If a ptosis correction is requested then an alternative procedure known as a mastopexy would be required which can occasionally be combined with an augmentation, albeit with certain increased risks. This, however, leads to additional incisions and hence scarring around the nipple and often lower breast (see photos of mastopexy or reduction on Mr Turton’s website), dependant on which technique is required. Care should be taken to discuss this with your surgeon should you wish the nipple position to be altered. Some women are happy to live with a degree of looseness and ptosis so long as the volume of the breast can be returned with the augmentation. So long as they understand that in a bra they will have good volume and projection but once the bra is removed they will have the downward deflection of the nipples as before. At all times it should be emphasised that we are aiming to achieve what the woman wants and not some preconceived idea of perfection. If you do not have ptosis then you will not have to worry about this, although it can develop later after augmentation and sometimes it can occur just in one breast causing asymmetry. Future weight changes, hormonal changes, the presence of implants and simple ageing can all contribute unpredictably to the way the breast behaves as you get older. This can affect women who do not have implants but is generally more obvious after augmentation.
Possibly. Revision or replacement may be required due to ageing, implant change, or complications.